DIAGNOSIS YEAR
Select the diagnosis year first. J’Onco Mentor uses it to establish the standards cycle and to drive year-sensitive routing in this module.
INTERACTIVE THYROID ANATOMY
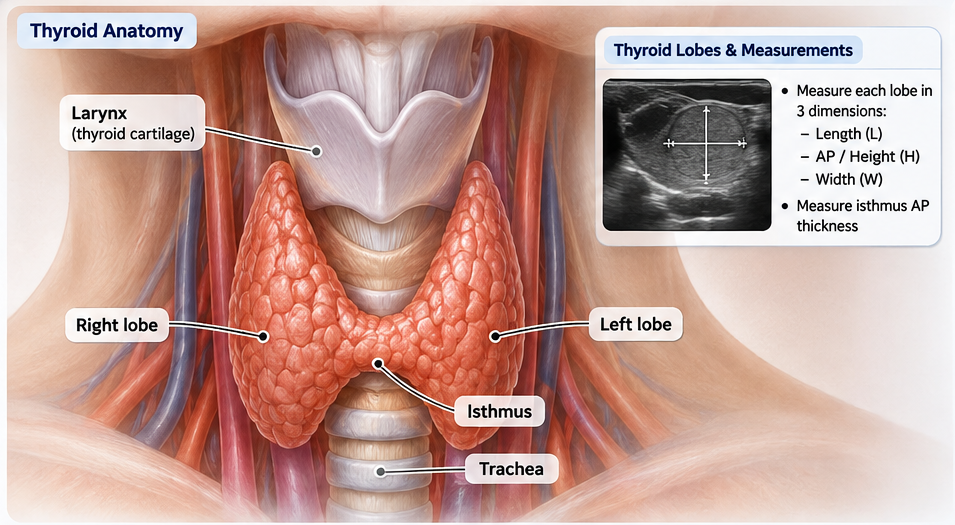
SELECT ONE OR MORE THYROID REGIONS
Select multiple regions directly, or use the anatomy hotspots/buttons. Right lobe + left lobe will display as bilateral involvement.
IMAGING — STANDARD THYROID VIEWS
2D Ultrasound
- Transverse views of each lobe: superior, mid, inferior.
- Longitudinal views of each lobe: medial, mid, lateral.
- Isthmus: transverse image with AP thickness measurement.
- Document nodules in at least two orthogonal planes with three-dimensional measurements.
3D / Volumetric Imaging
- Acquire a volumetric dataset when 3D imaging is used.
- Reconstruct in axial/transverse, sagittal/longitudinal and coronal planes.
- Use the volumetric views to supplement, not replace, standard diagnostic documentation.
THYROID HISTOLOGY / SCHEMA ROUTING
SELECTED HISTOLOGY
SCHEMA / AJCC ROUTING
Select histology.
For 2026, differentiated and anaplastic thyroid carcinomas use AJCC 8 Chapter 73; medullary thyroid carcinoma uses AJCC 8 Chapter 74 when eligible.
BETHESDA / ODS REPORTABILITY
REPORTABILITY RESULT
Select a Bethesda category.
BRAF / MOLECULAR — THYROID
BRAF V600E
Most strongly associated with papillary thyroid carcinoma and can also occur in some poorly differentiated or anaplastic thyroid carcinomas.
ODS REPORTABILITY
A positive BRAF result alone does not automatically establish a reportable thyroid cancer diagnosis. Genetic findings without pathologic or clinical evidence of reportable disease are risk/prognostic information, not a diagnosis.
What to look for
Look for a reportable pathology/cytology diagnosis or a recognized medical practitioner's clinical diagnosis of malignancy. Bethesda VI is reportable in the absence of contrary information; Bethesda V requires additional confirmation.
AJCC STAGING
PATHOLOGIC STAGING CRITERIA — THYROID
Qualifying evidence: Thyroid lobectomy or thyroidectomy generally supports pathological evaluation of primary tumor extent (pT). Examined regional lymph nodes can support pN. Age, histologic type, and the applicable chapter affect stage grouping.
pT / pN: Assign only categories supported by the actual pathological evidence and the site-specific AJCC rules. A diagnosis-confirming biopsy does not automatically establish a pathological primary tumor category.
pM: Pathologically proven distant metastasis may support pM1 where the chapter permits; AJCC does not use pM0.
Treatment sequence: Distinguish initial pathological classification (pTNM) from post-neoadjuvant classification (ypTNM). Confirm eligibility, histology, staging chapter and diagnosis-year edition before finalizing.
Source / verification: AJCC · SEER tools and manuals. Educational overview only; verify exact chapter-specific criteria in the licensed AJCC manual.
Thyroid AJCC staging schema / TNM context
Use the T, N and M controls and site-specific factors below. Verify final AJCC ID, TNM edition and stage group in the approved AJCC/SEER staging system for the diagnosis year.
AJCC RESULT
Select histology and staging inputs.
| AJCC ID | — |
|---|---|
| TNM Edition | — |
REGIONAL LYMPH NODES
Central compartment
Prelaryngeal, pretracheal and paratracheal nodes; Level VI and upper mediastinal Level VII are central compartment nodes.
Lateral neck
Levels I–V are lateral cervical nodal groups. Exact N category depends on histologic staging system.
ODS reminder
Do not infer N category solely from the word “cervical.” Use the documented nodal level/location and the applicable AJCC/EOD schema.
EOD / SUMMARY STAGE
SEER*RSA
Thyroid gland C73.9 routes to the appropriate thyroid EOD schema based on histology, including differentiated/anaplastic versus medullary pathways.
Summary Stage
Use the diagnosis-year SEER*RSA tables for exact localized, regional and distant definitions. Do not convert AJCC stage groups directly into Summary Stage.
SURGERY — THYROID GLAND (2026)
COMMON METASTATIC SITES — THYROID
Lung
Common distant site, especially for differentiated thyroid carcinoma.
Bone
Frequent site of distant spread in differentiated and medullary disease.
Liver
Can occur in advanced thyroid malignancy.
Brain
Less common but recognized distant metastatic site.